High-Risk Medication Consent
Asks about prescribing provider, medication name and dosage, and condition being treated. Built for pain management clinics initiating opioid therapy.
- Questions
- 14
- Pages
- 2
- Time
- about 4 min
Includes
- E-signature
- Medication list
Your practice
High-Risk Medication Consent
Page 1 of 2 · Your information
Live preview. Tap through it like a patient.
Who it is for
- Pain management clinics initiating opioid therapy
- Rheumatology practices prescribing biologics and immunosuppressants
- Dermatology offices managing isotretinoin (iPLEDGE) patients
- Oncology centers documenting chemotherapy consent
What's inside
Before you publish: Add your practice-approved consent wording before publishing.
Page 1 · Your information
- Patient NameText · Required
- Date of BirthDate
- Prescribing ProviderText
- Medication Name and DosageMedications
- Condition Being TreatedText
Page 2 · Additional details
- Lab Monitoring Schedule AgreedLong Text
- Pregnancy Prevention AcknowledgmentLong Text
- Alternative Treatments DiscussedLong Text
- Patient Education Materials ReceivedLong Text
- Patient Questions AddressedLong Text
From form to a ready patient
01
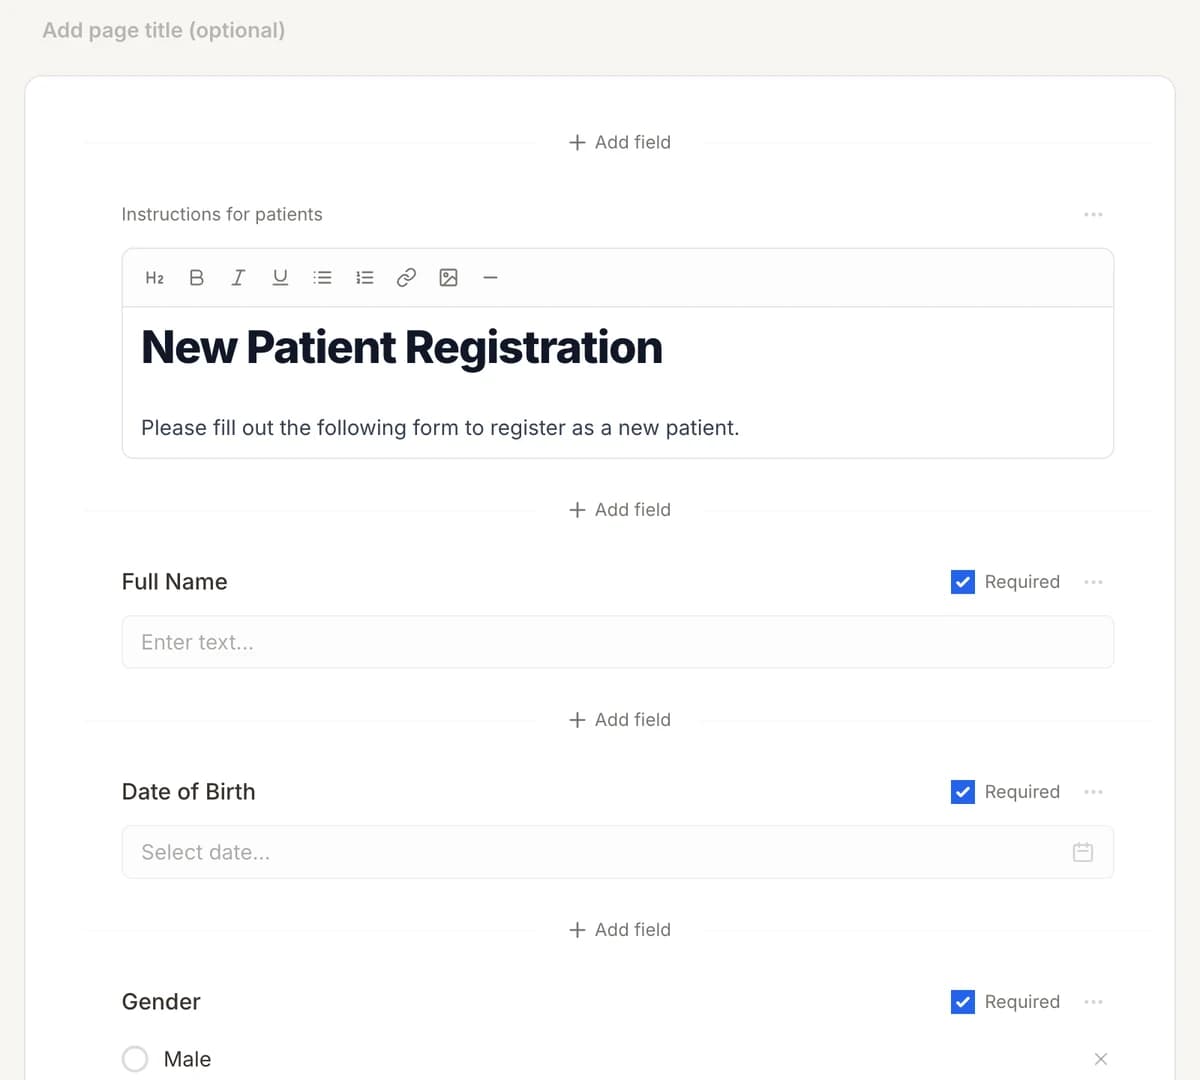
Make it yours
Reword, reorder, or add to the High-Risk Medication Consent, and add your logo.
02
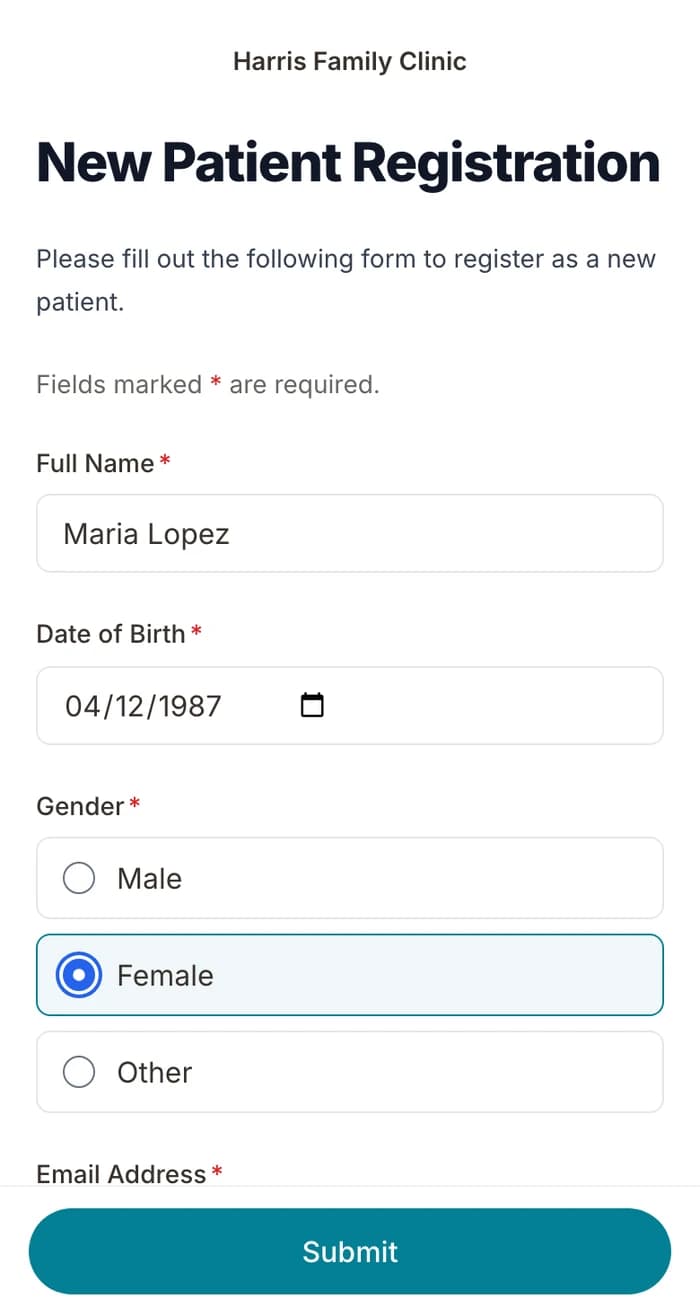
Patients finish it at home
A secure link by text or email, filled out on their phone before the visit. No app.
03
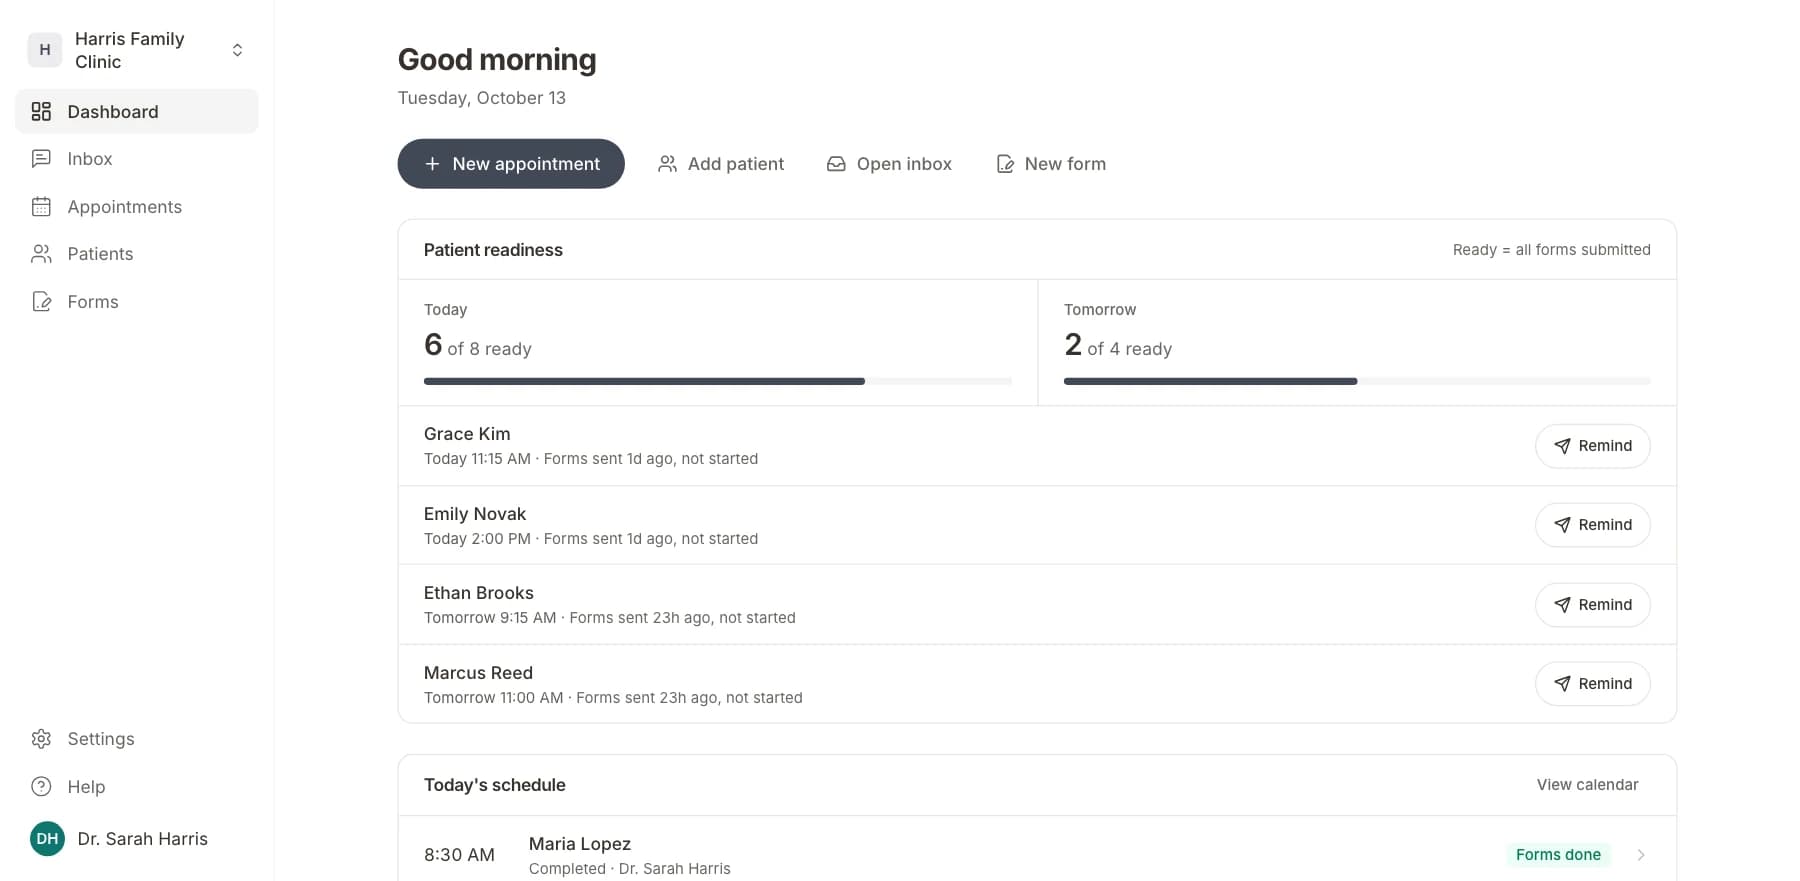
Your team sees who is ready
Each visit shows as ready once its forms are in. Answers land on the patient record.
Related templates
All templatesQuestions
Send it before the visit, so patients arrive ready.
Add the High-Risk Medication Consent to your account and make it yours in a few minutes.
Cancel anytime · BAA included