Pharmacy Transfer Request Form
Asks about current pharmacy name, current pharmacy phone, and medications to transfer. Built for retail pharmacy chains.
- Questions
- 10
- Page
- 1
- Time
- about 3 min
Includes
- E-signature
- Insurance details
- Medication list
Your practice
Pharmacy Transfer Request Form
Insurance Information
Live preview. Tap through it like a patient.
Who it is for
- Retail Pharmacy Chains
- Independent Pharmacies
- Hospital Outpatient Pharmacies
- Specialty Pharmacy Services
- Mail-Order Pharmacies
What's inside
- Patient Full NameText · Required
- Date of BirthDate
- Phone NumberPhone
- Current Pharmacy NameText
- Current Pharmacy PhonePhone
- Medications to TransferMedications
- New Pharmacy LocationText
- Insurance InformationInsurance Info
- Email AddressEmail
- Transfer AuthorizationE-Signature
From form to a ready patient
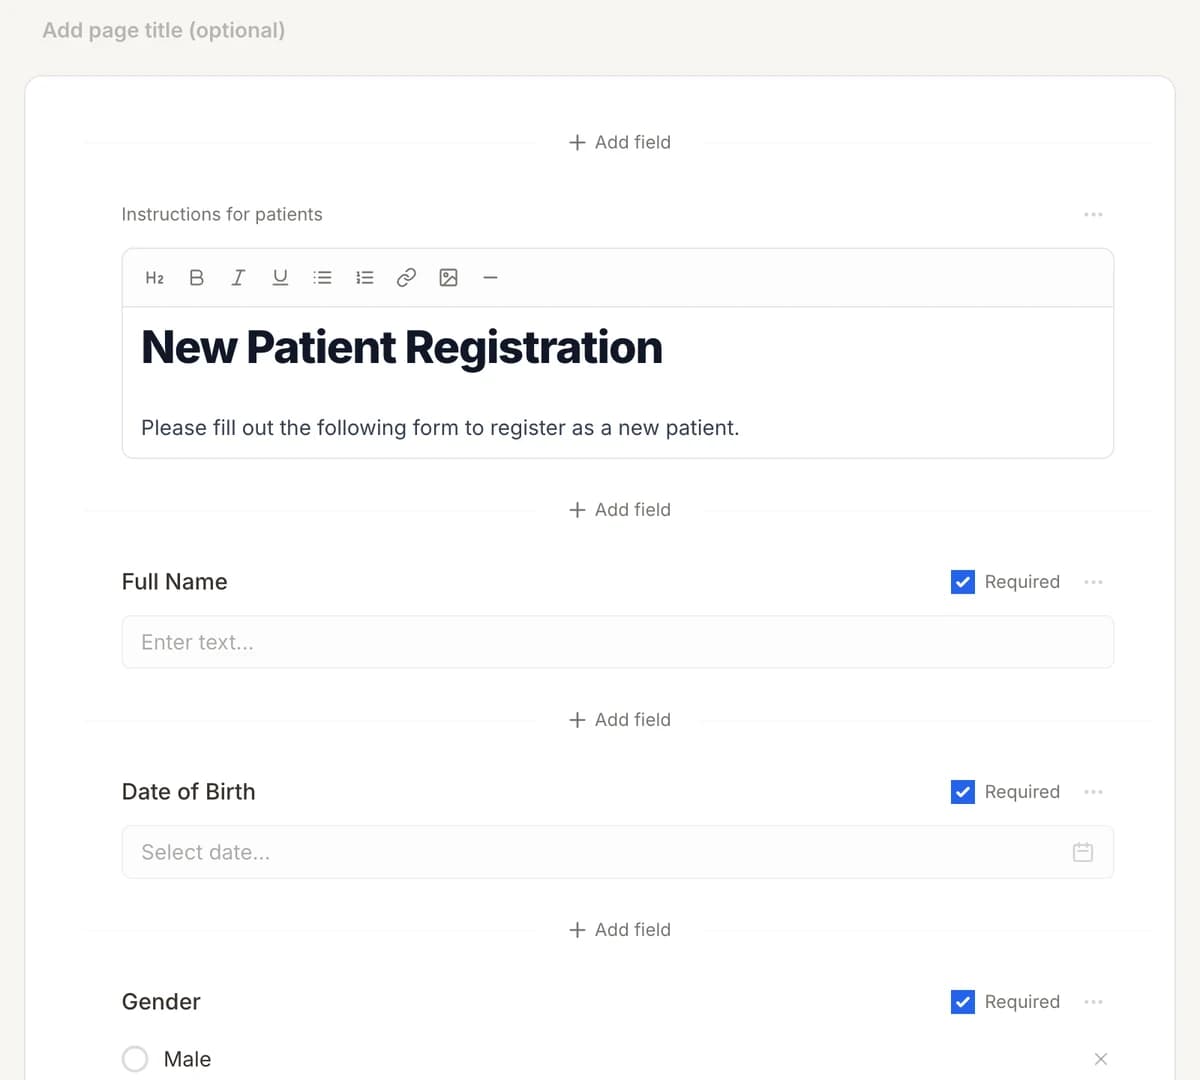
01
Make it yours
Reword, reorder, or add to the Pharmacy Transfer Request Form, and add your logo.
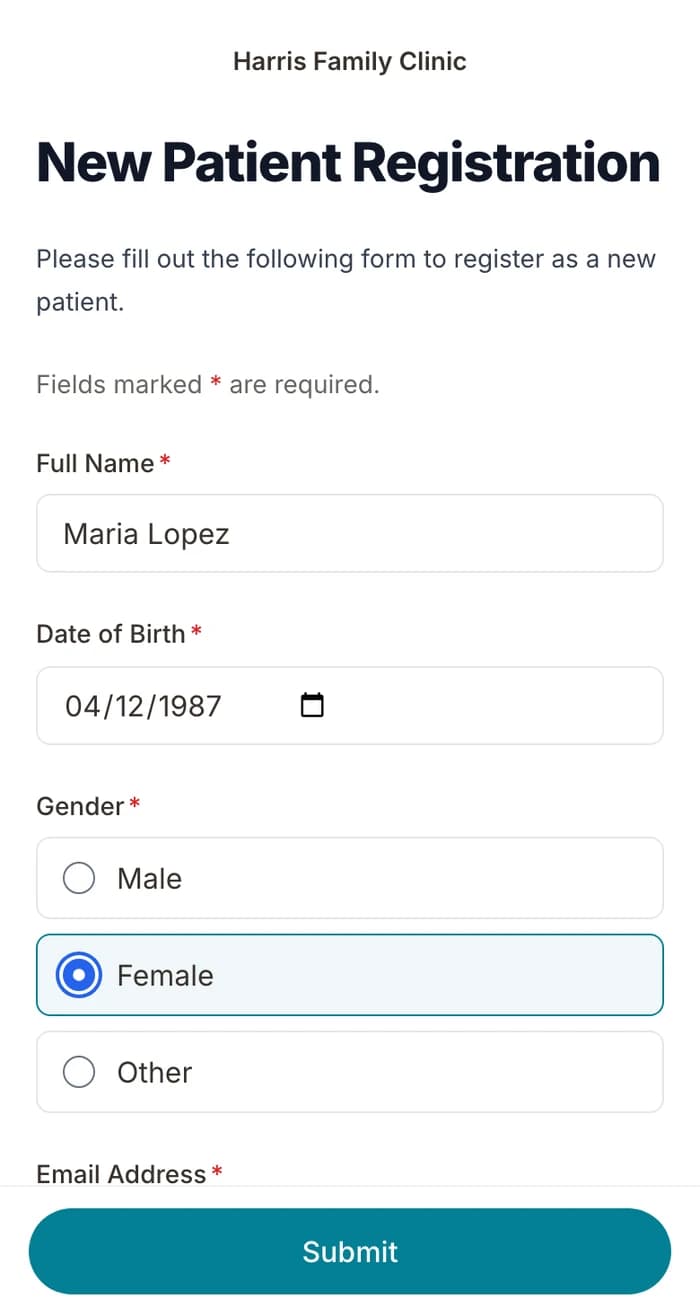
02
Patients finish it at home
A secure link by text or email, filled out on their phone before the visit. No app.
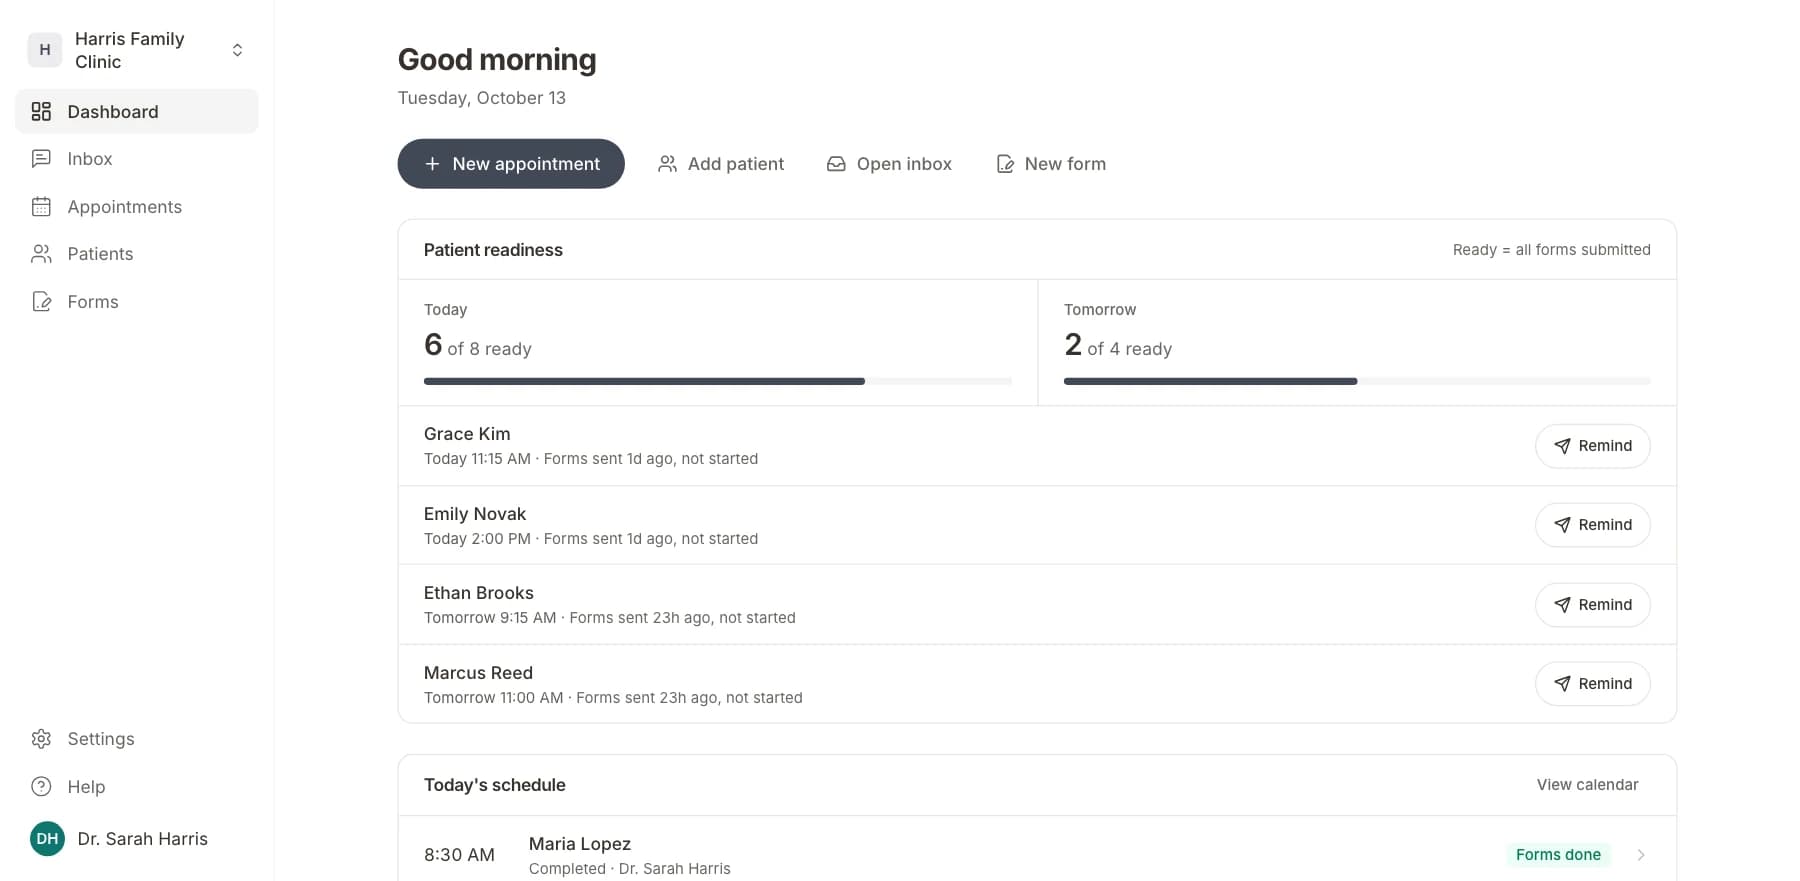
03
Your team sees who is ready
Each visit shows as ready once its forms are in. Answers land on the patient record.
Related templates
All templatesMedication Refill Request FormRegistration · 8 questions
Insurance Verification FormIntake · 8 questions
Specialty Pharmacy Enrollment FormRegistration · 10 questions
Patient Portal Registration FormRegistration · 10 questions
Advance Directive FormRegistration · 14 questions
Appointment Request FormRegistration · 11 questions
Questions
Send it before the visit, so patients arrive ready.
Add the Pharmacy Transfer Request Form to your account and make it yours in a few minutes.
Cancel anytime · BAA included