Fall Risk Screening Form
Asks about fall history (Past 12 months), fall circumstances & injuries, and current medications (Count). Built for geriatric and senior care practices.
- Questions
- 10
- Page
- 1
- Time
- about 3 min
Includes
- Medication list
Your practice
Fall Risk Screening Form
Live preview. Tap through it like a patient.
Who it is for
- Geriatric and senior care practices
- Primary care annual wellness visits for 65+
- Home health and visiting nurse services
- Skilled nursing and rehabilitation facilities
What's inside
Before you publish: Clinical review required: this worksheet does not calculate scores, diagnose, or recommend treatment. Confirm the questions and response options against your approved assessment protocol before use.
- Full NameText · Required
- Fall History (Past 12 Months)Long Text
- Fall Circumstances & InjuriesLong Text
- Current Medications (Count)Number
- High-Risk MedicationsMedications
- Balance & Mobility ConfidenceLong Text
- Vision ConcernsLong Text
- Home Environmental HazardsLong Text
- Fear of FallingLong Text
- Assessment DateDate
From form to a ready patient
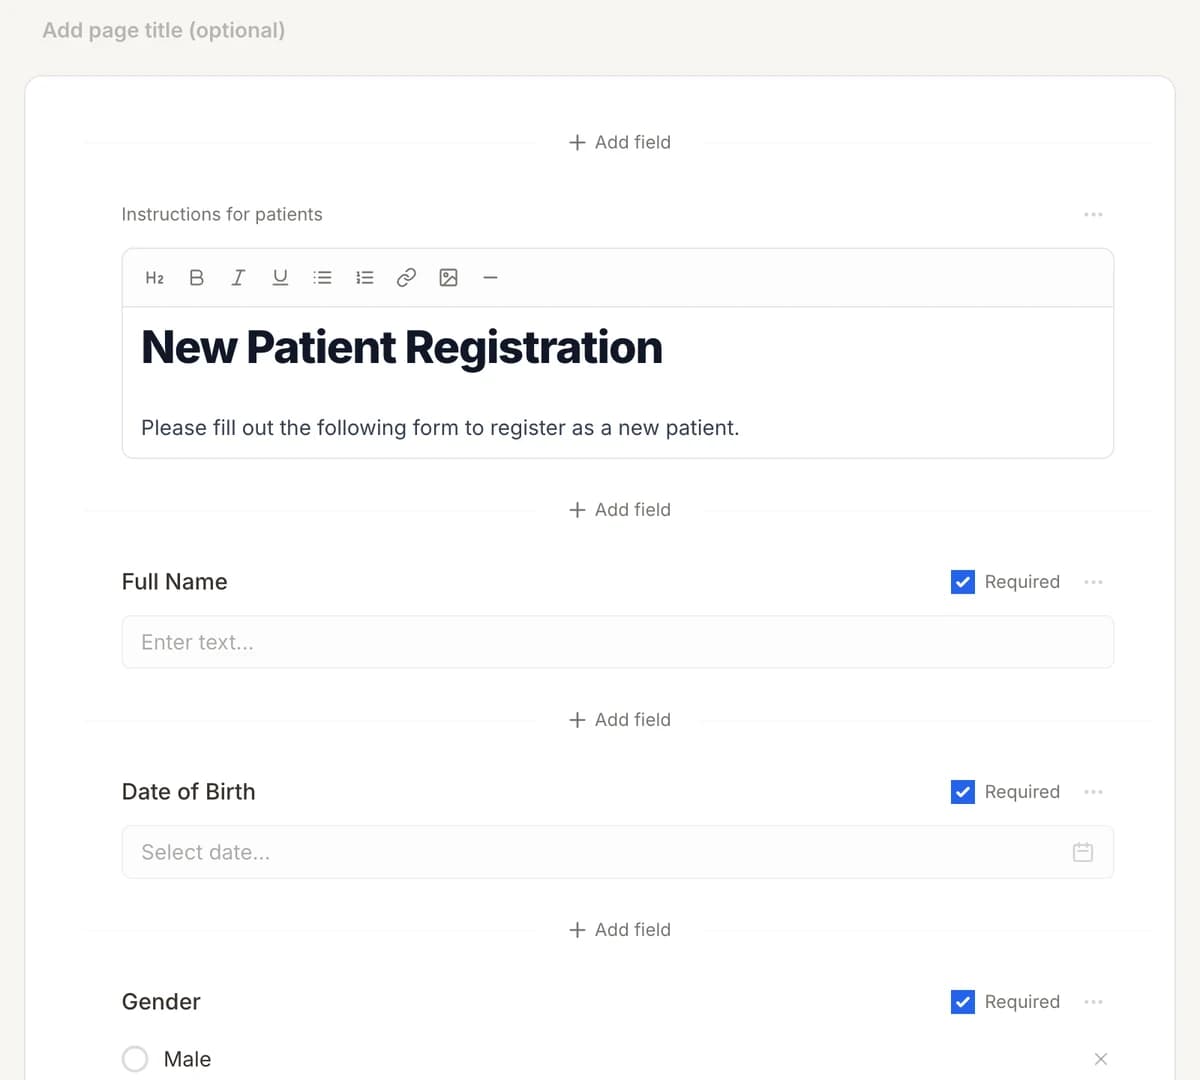
01
Make it yours
Reword, reorder, or add to the Fall Risk Screening Form, and add your logo.
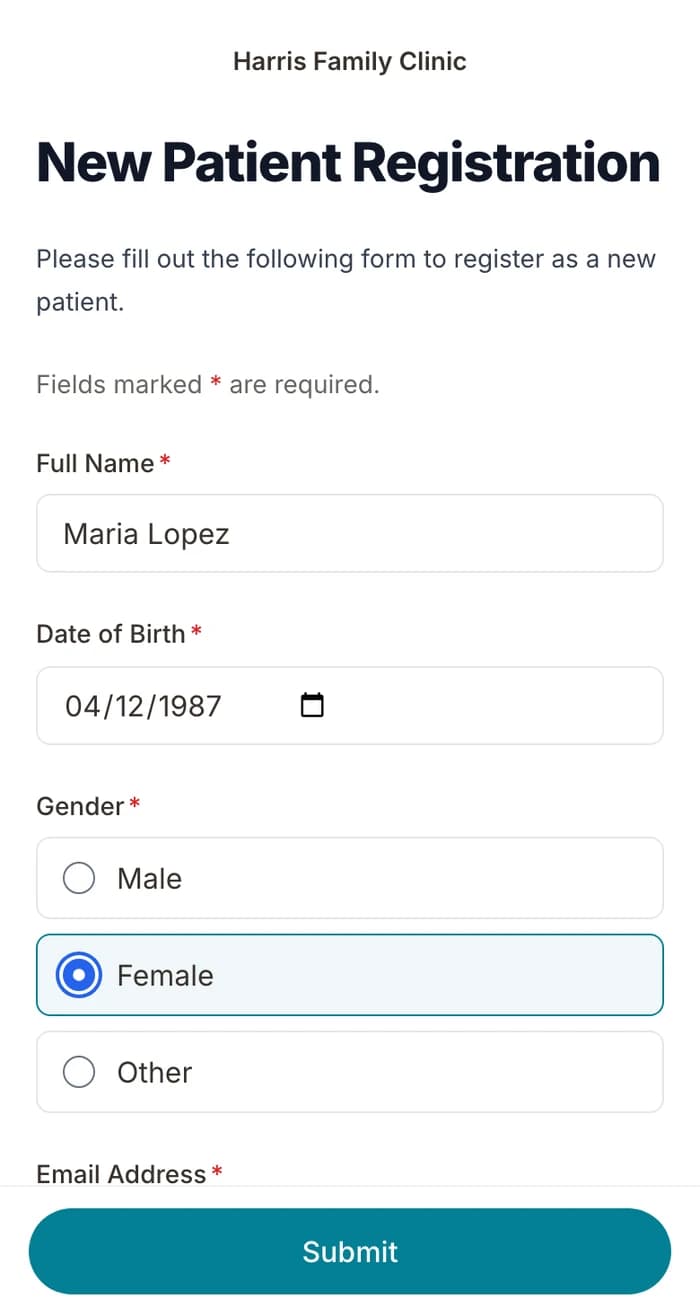
02
Patients finish it at home
A secure link by text or email, filled out on their phone before the visit. No app.
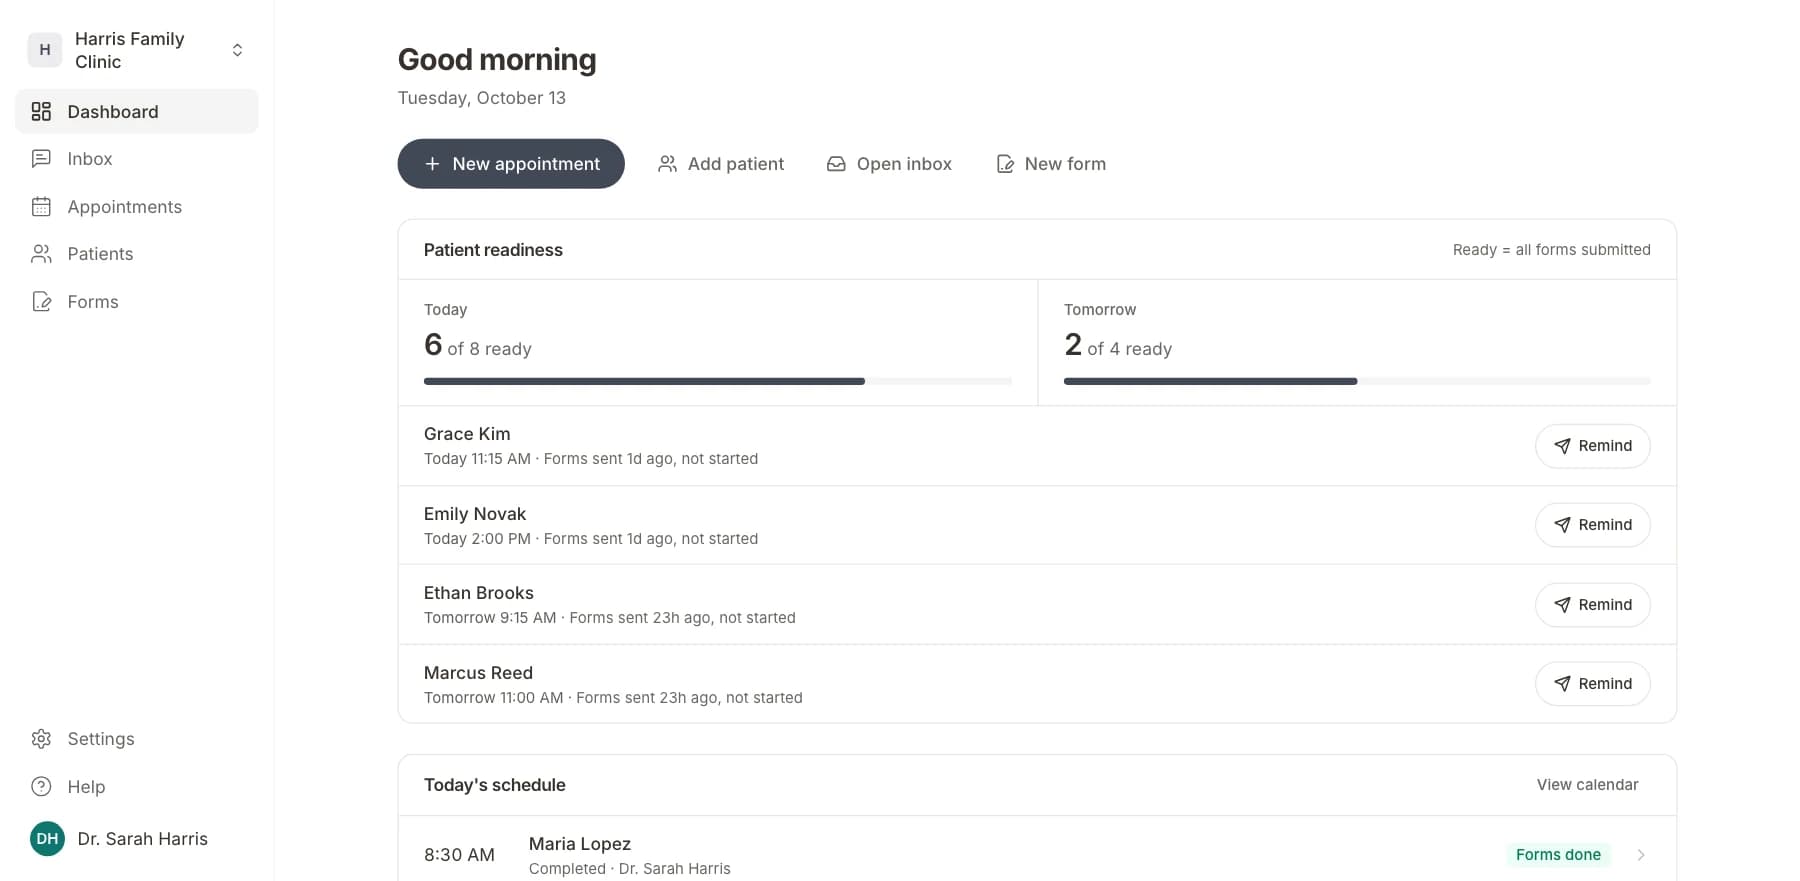
03
Your team sees who is ready
Each visit shows as ready once its forms are in. Answers land on the patient record.
Related templates
All templatesFall Risk Assessment (Morse Fall Scale)Assessment · 14 questions
Geriatric Depression Scale (GDS) FormScreening · 15 questions
Geriatrics Intake FormIntake · 17 questions
Cardiac Risk Assessment FormAssessment · 16 questions
Activities of Daily Living (ADL) Assessment FormAssessment · 14 questions
Osteoporosis and Fracture History FormMedical History · 10 questions
Questions
Send it before the visit, so patients arrive ready.
Add the Fall Risk Screening Form to your account and make it yours in a few minutes.
Cancel anytime · BAA included