Pediatric Ophthalmology Medical History Form
Asks about child's full name, parent/guardian name, and primary vision concern. Built for pediatric ophthalmology clinics.
- Questions
- 8
- Page
- 1
- Time
- about 2 min
Includes
- Medication list
- Conditions checklist
Your practice
Pediatric Ophthalmology Medical History Form
Live preview. Tap through it like a patient.
Who it is for
- Pediatric ophthalmology clinics
- Children's hospital eye departments
- Strabismus and amblyopia specialists
- Pediatric retina specialists
- Congenital eye disorder clinics
What's inside
- Child's Full NameText
- Date of BirthDate
- Parent/Guardian NameText
- Primary Vision ConcernLong Text
- Birth HistoryLong Text
- Previous Eye SurgeriesLong Text
- Family Eye Disease HistoryConditions
- Current MedicationsMedications
From form to a ready patient
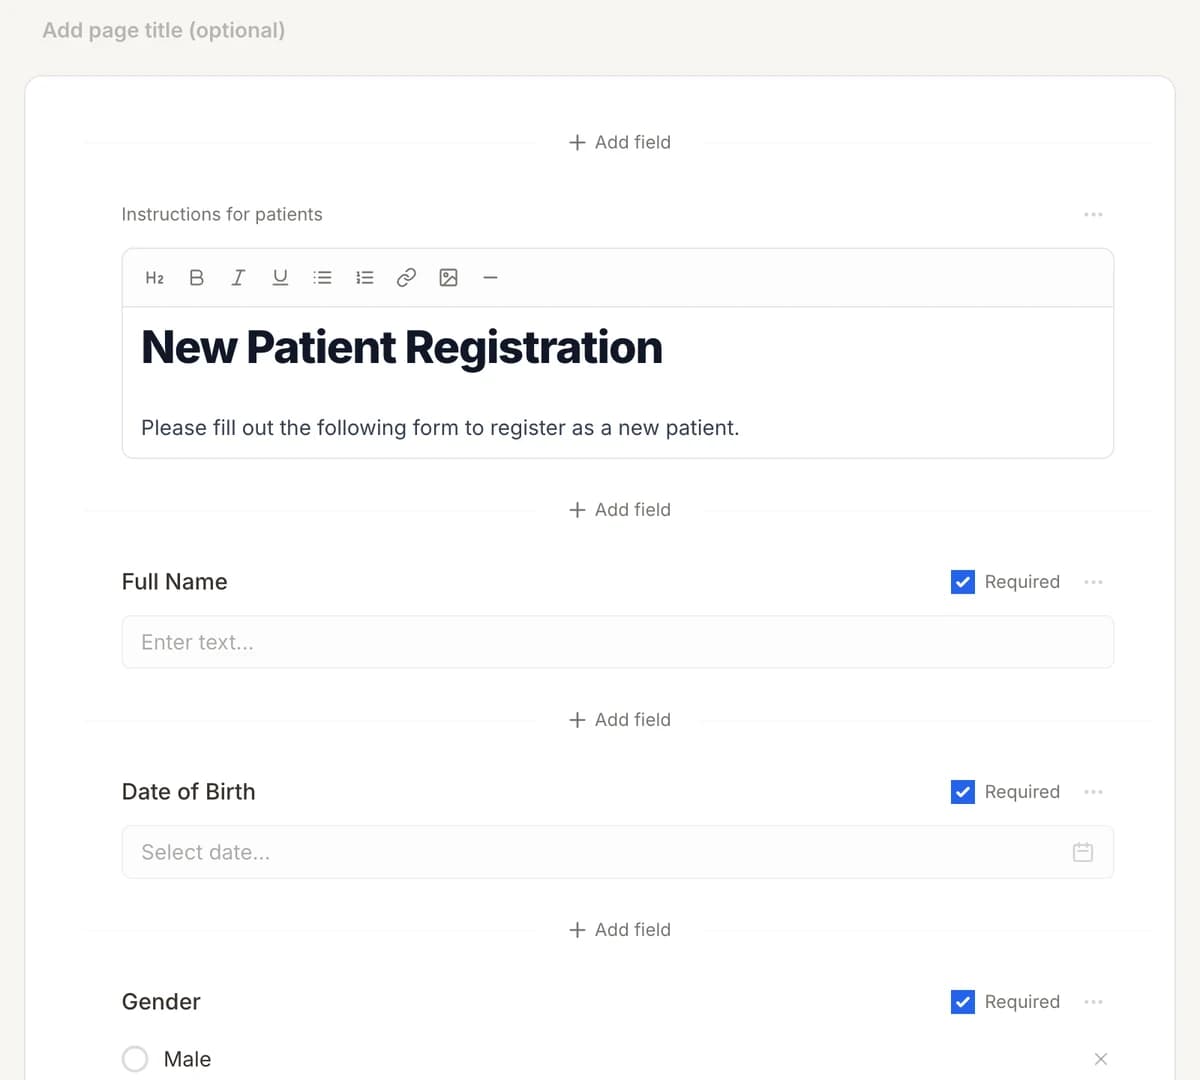
01
Make it yours
Reword, reorder, or add to the Pediatric Ophthalmology Medical History Form, and add your logo.
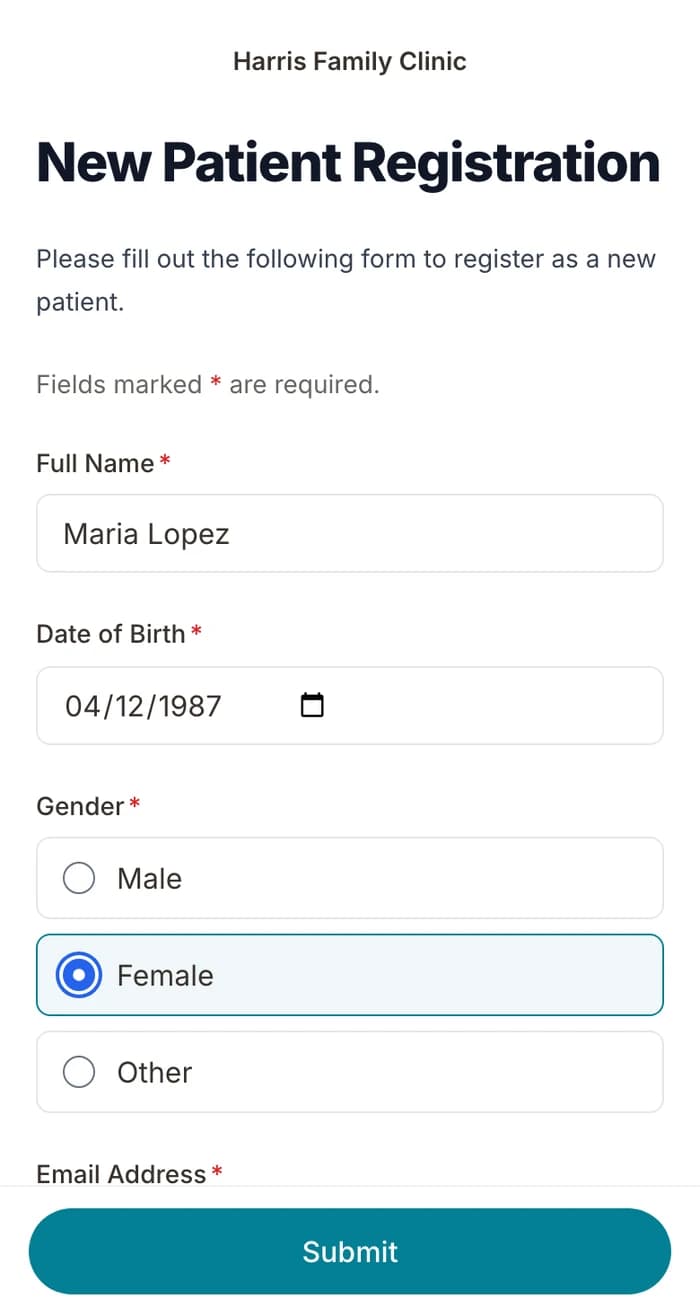
02
Patients finish it at home
A secure link by text or email, filled out on their phone before the visit. No app.
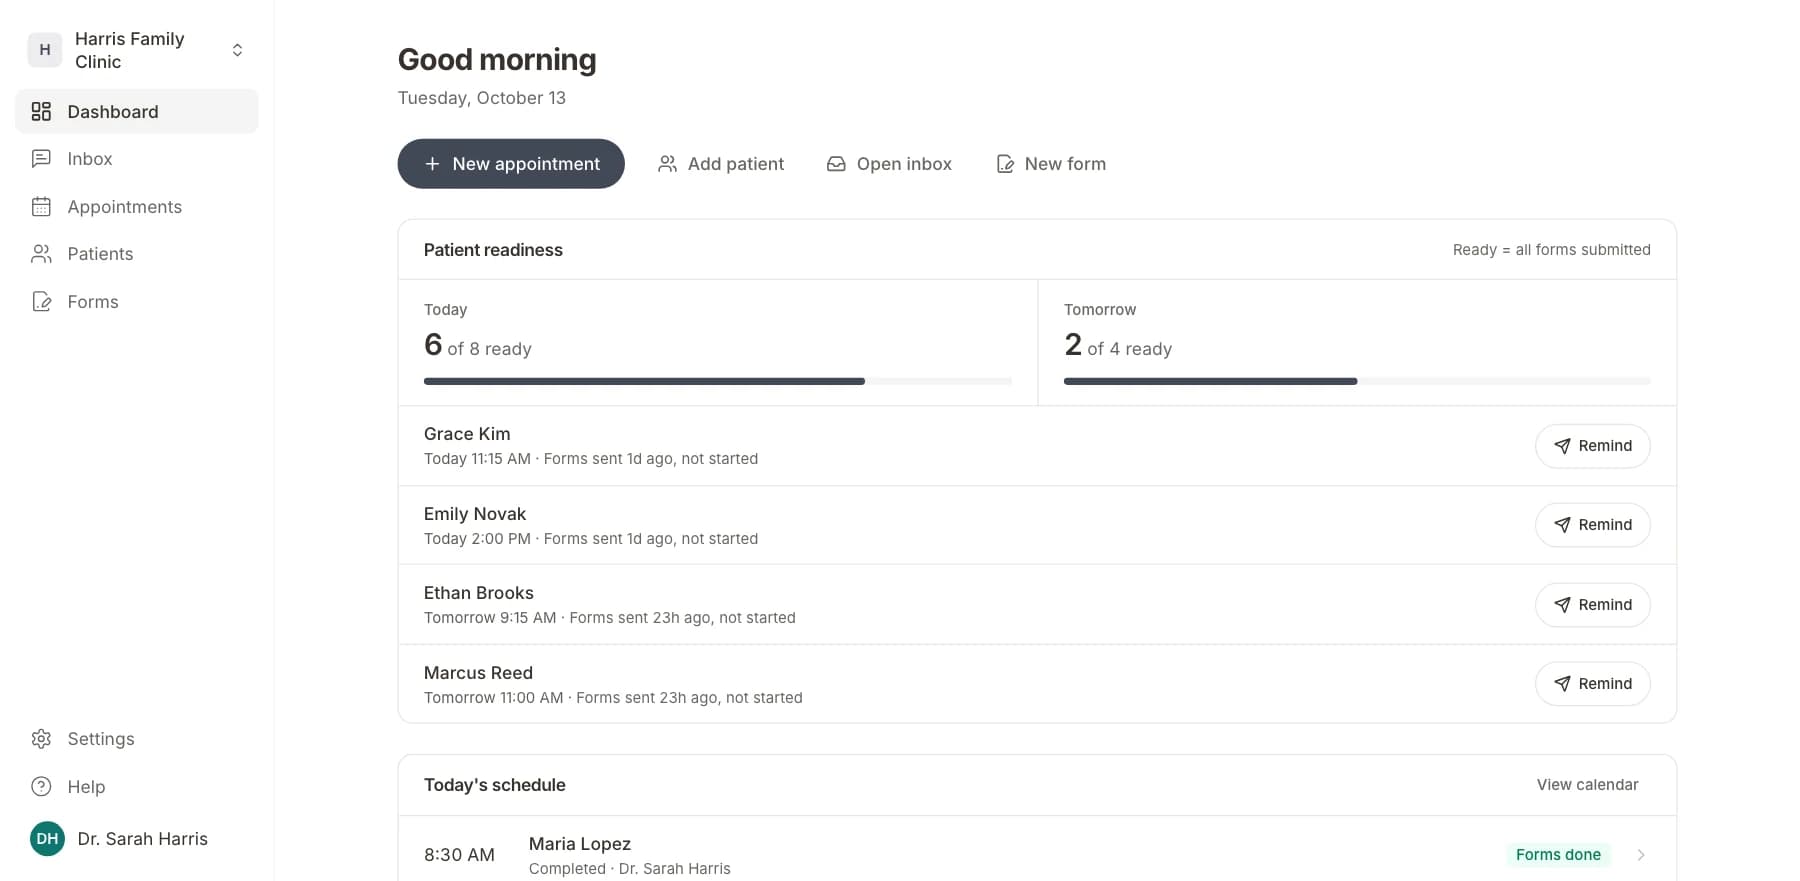
03
Your team sees who is ready
Each visit shows as ready once its forms are in. Answers land on the patient record.
Related templates
All templatesPediatric Medical History FormMedical History · 18 questions
Ophthalmology Intake FormIntake · 15 questions
Pediatric Intake FormIntake · 10 questions
Vision Therapy Initial Assessment FormAssessment · 10 questions
Neonatal Assessment FormAssessment · 18 questions
Allergy History FormMedical History · 10 questions
Questions
Send it before the visit, so patients arrive ready.
Add the Pediatric Ophthalmology Medical History Form to your account and make it yours in a few minutes.
Cancel anytime · BAA included