Referral Request Form
Asks about policy number, referring provider name, and referred to (Specialist/Provider). Built for primary care referrals to specialists.
- Questions
- 17
- Page
- 1
- Time
- about 4 min
Includes
- File upload
Your practice
Live preview. Tap through it like a patient.
Who it is for
- Primary care referrals to specialists
- Inter-departmental referrals within health systems
- Diagnostic imaging and lab referral coordination
- Care coordination for multi-specialty patient management
What's inside
- Patient NameText · Required
- Date of BirthDate · Required
- Phone NumberPhone · Required
- EmailEmail
- Insurance ProviderText
- Policy NumberText
- Referring Provider NameText · Required
- Referred To (Specialist/Provider)Text · Required
- SpecialtyDropdown · 15 choices · Required
- UrgencyMultiple Choice · 3 choices · Required
From form to a ready patient
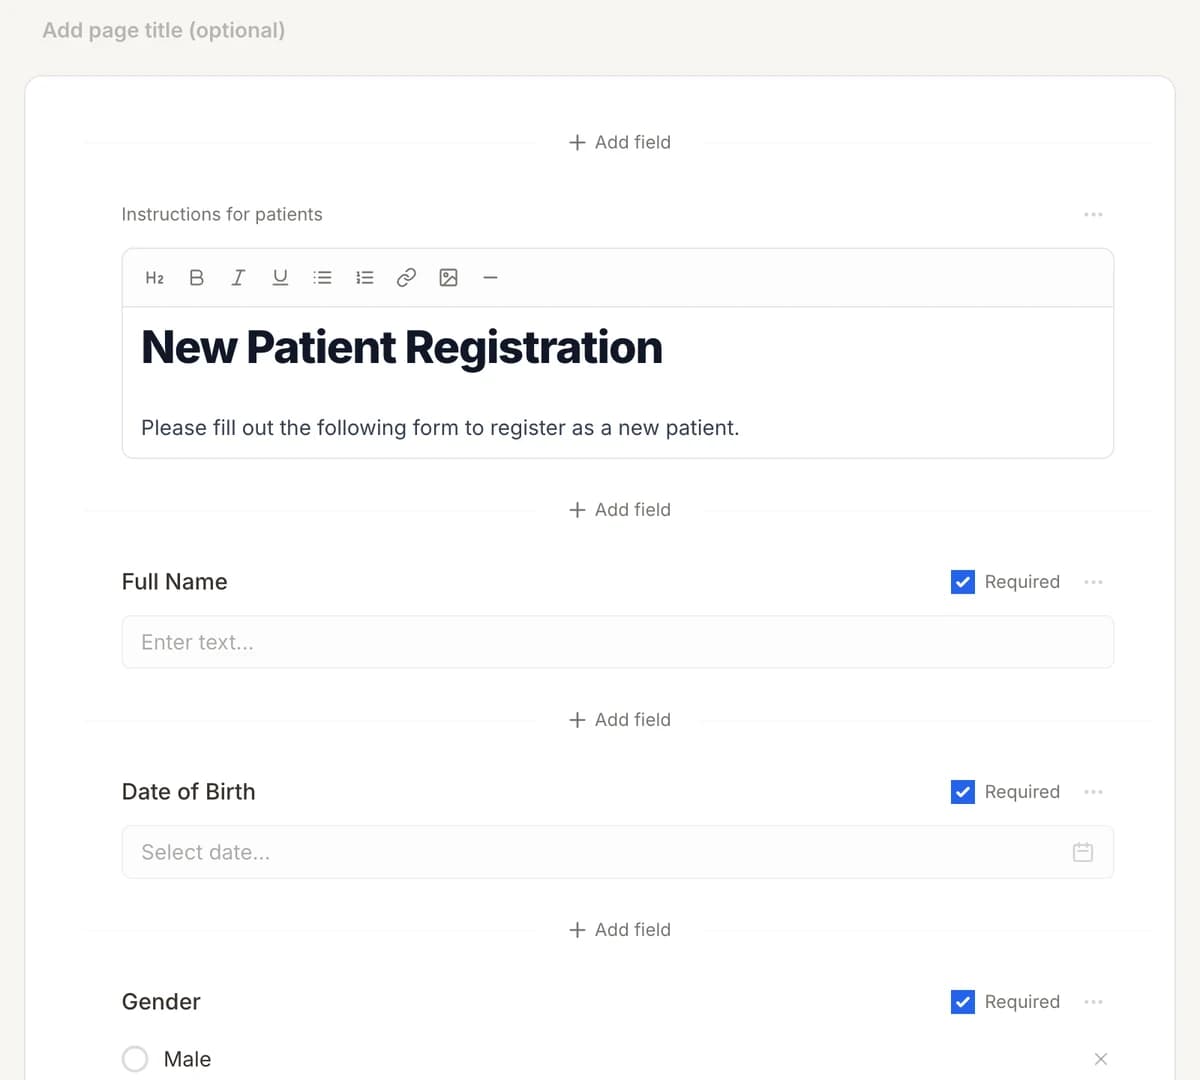
01
Make it yours
Reword, reorder, or add to the Referral Request Form, and add your logo.
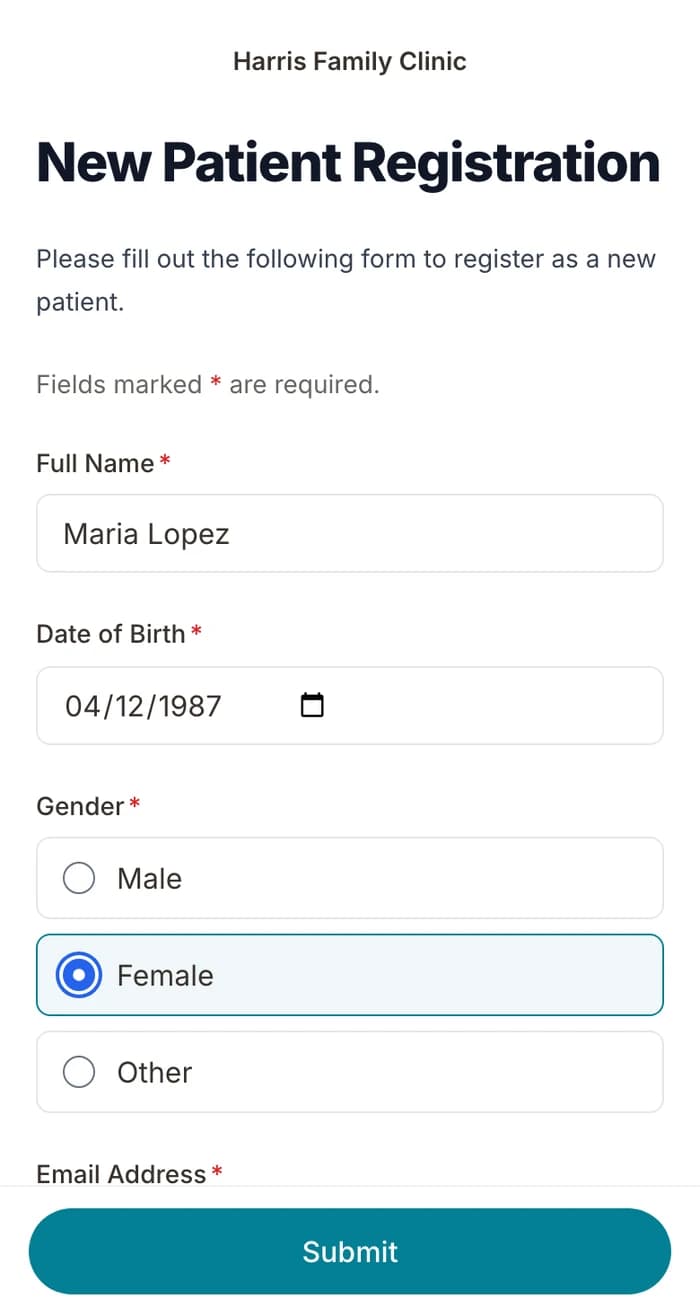
02
Patients finish it at home
A secure link by text or email, filled out on their phone before the visit. No app.
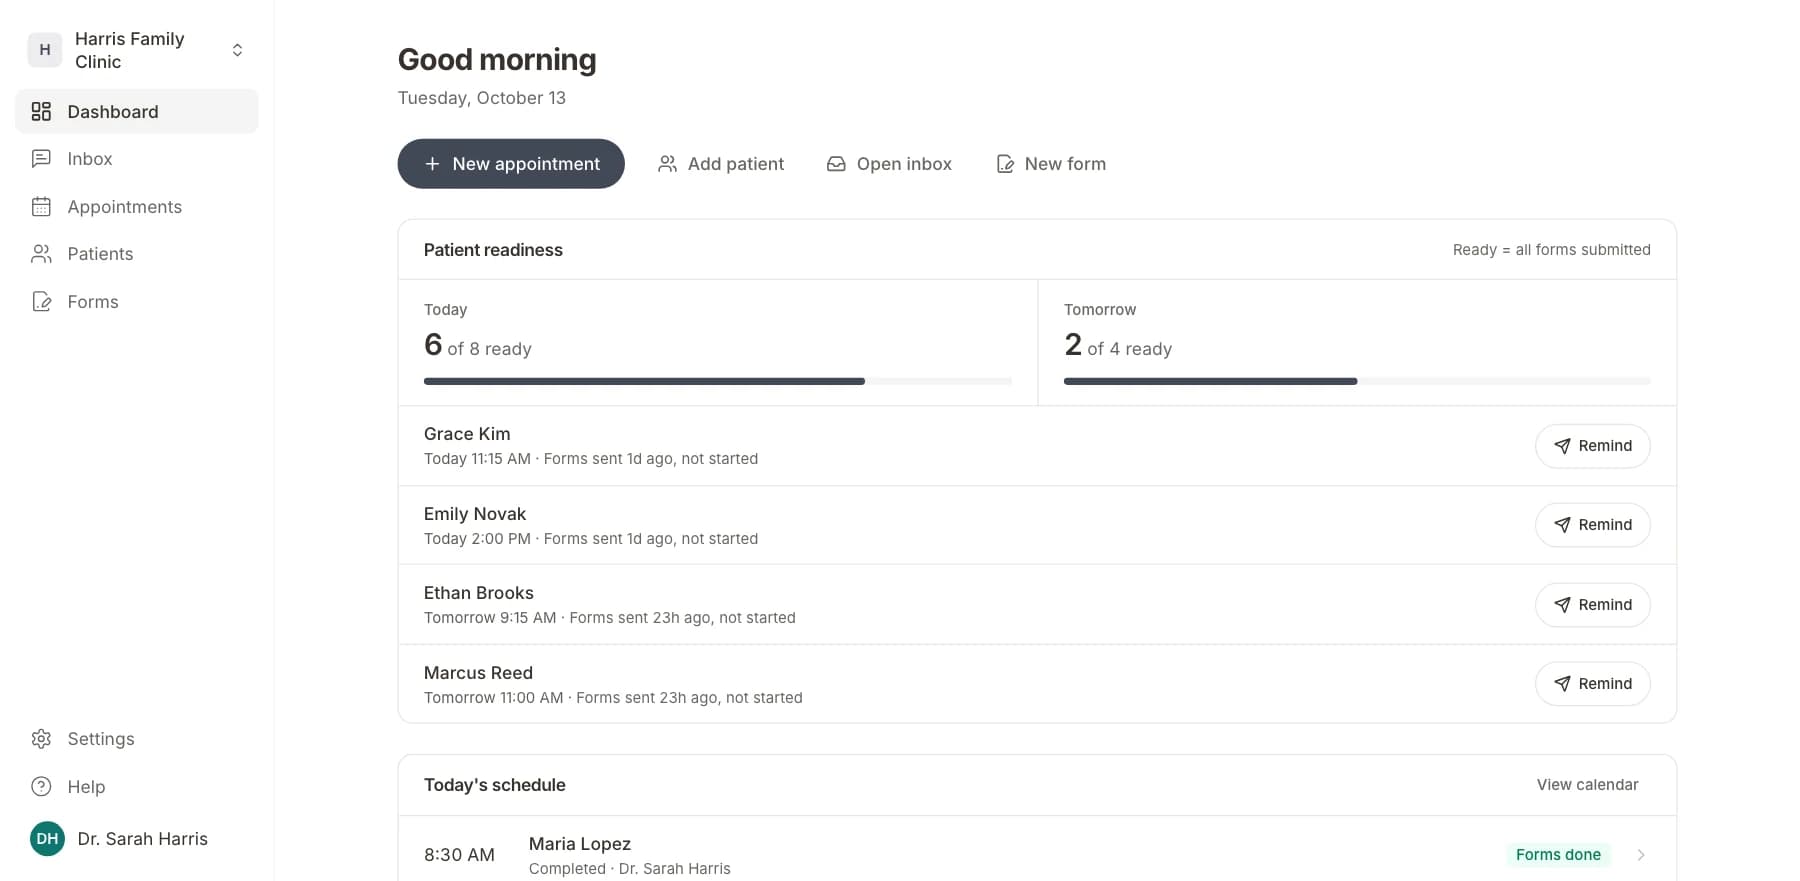
03
Your team sees who is ready
Each visit shows as ready once its forms are in. Answers land on the patient record.
Related templates
All templatesReferral Feedback SurveySurvey · 10 questions
Appointment Request FormRegistration · 11 questions
Patient Transfer Request FormRegistration · 14 questions
Pharmacy Transfer Request FormRegistration · 10 questions
Advance Directive FormRegistration · 14 questions
Clinical Trial Enrollment FormRegistration · 15 questions
Questions
Send it before the visit, so patients arrive ready.
Add the Referral Request Form to your account and make it yours in a few minutes.
Cancel anytime · BAA included