Vision Therapy Initial Assessment Form
Asks about primary vision concern, reading difficulties, and double vision. Built for behavioral optometry practices.
- Questions
- 10
- Page
- 1
- Time
- about 3 min
Your practice
Vision Therapy Initial Assessment Form
Live preview. Tap through it like a patient.
Who it is for
- Behavioral Optometry Practices
- Pediatric Eye Care Centers
- Occupational Therapy Clinics
- Neuro-Optometry Specialists
- School Vision Programs
Formisoft for Mental HealthFormisoft for OptometryFormisoft for Pediatrics
What's inside
Before you publish: Clinical review required: this worksheet does not calculate scores, diagnose, or recommend treatment. Confirm the questions and response options against your approved assessment protocol before use.
- Patient NameText · Required
- Date of BirthDate
- Primary Vision ConcernLong Text
- Reading DifficultiesLong Text
- Double Vision?Multiple Choice · 3 choices
- Headaches with Near Work?Multiple Choice · 3 choices
- Eye Strain SymptomsLong Text
- Academic Performance ImpactLong Text
- Previous Eye ExamsLong Text
- Assessor NameText
From form to a ready patient
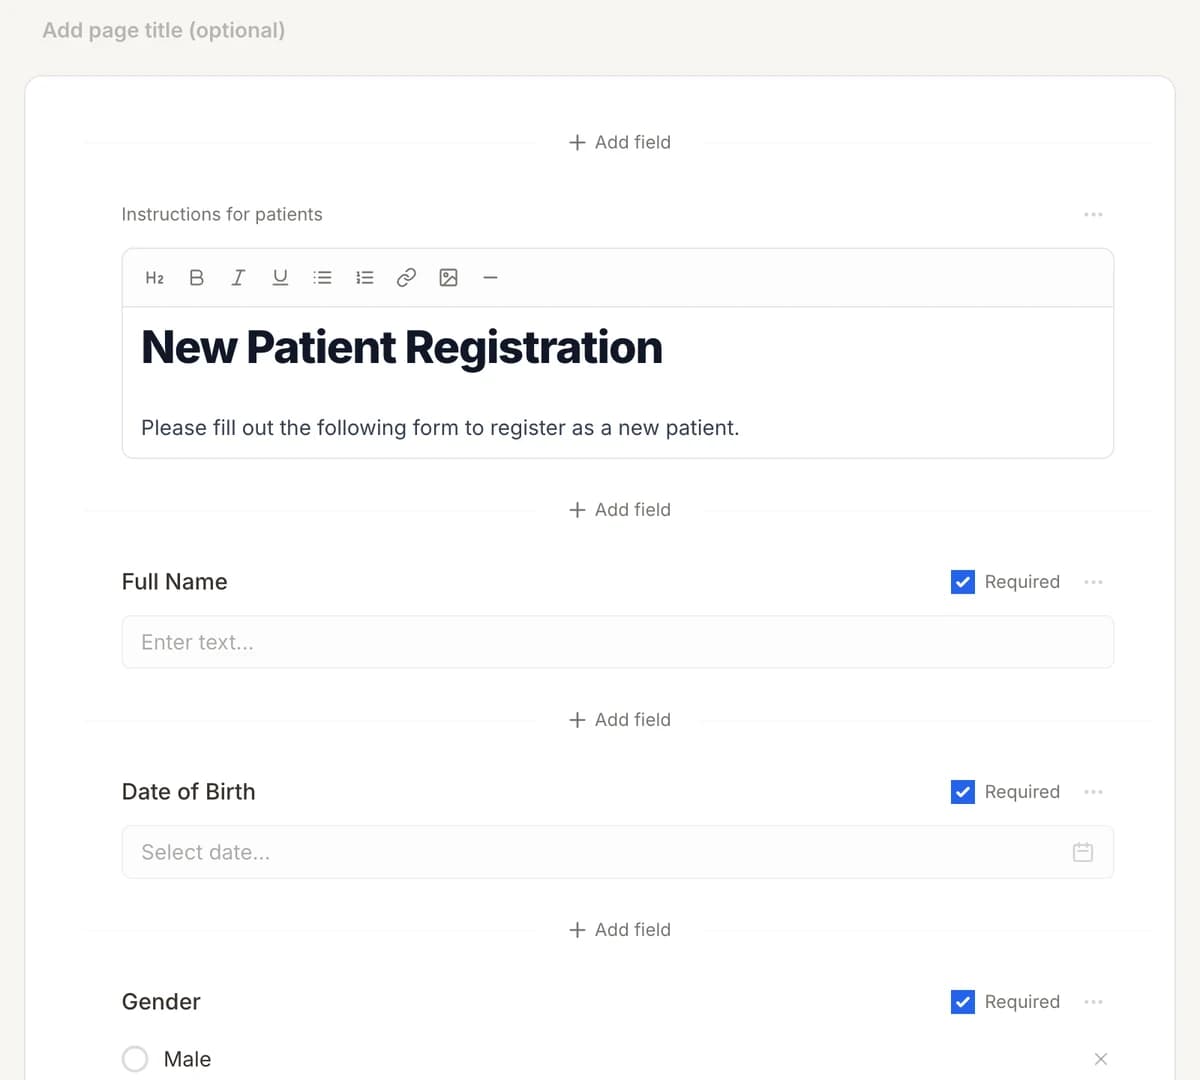
01
Make it yours
Reword, reorder, or add to the Vision Therapy Initial Assessment Form, and add your logo.
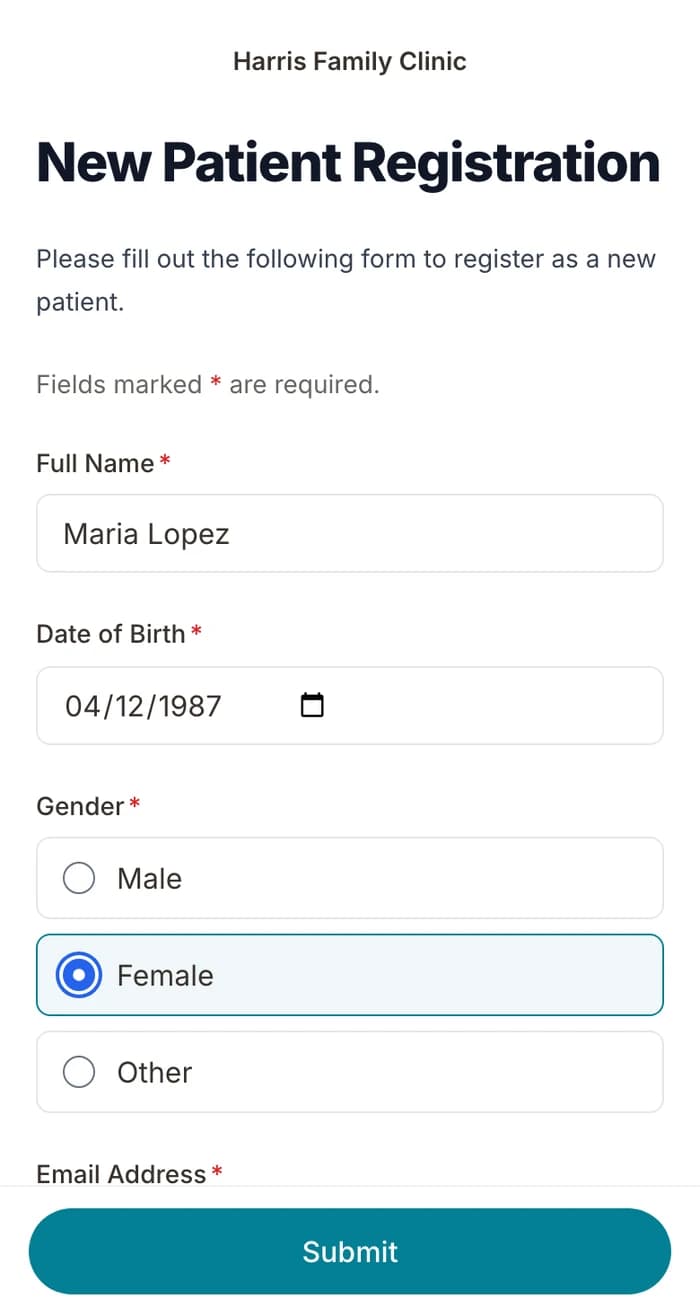
02
Patients finish it at home
A secure link by text or email, filled out on their phone before the visit. No app.
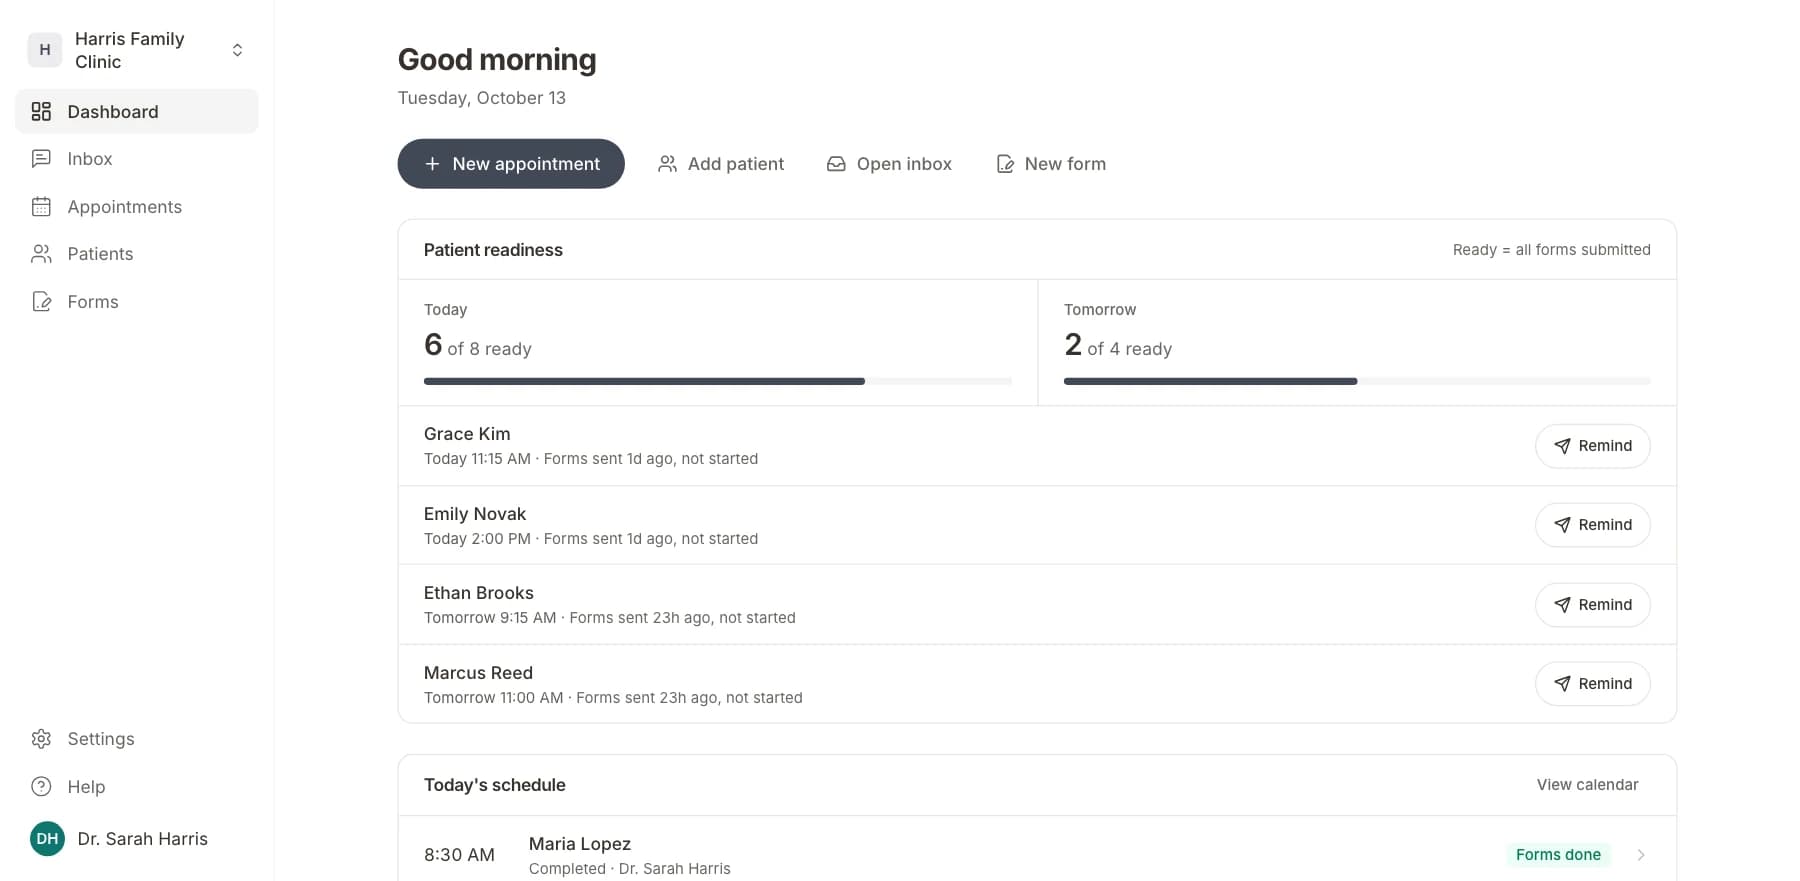
03
Your team sees who is ready
Each visit shows as ready once its forms are in. Answers land on the patient record.
Related templates
All templatesOphthalmology Intake FormIntake · 15 questions
Pediatric Intake FormIntake · 10 questions
Concussion SCAT Assessment FormAssessment · 16 questions
Occupational Therapy Intake FormIntake · 16 questions
Pediatric Ophthalmology Medical History FormMedical History · 8 questions
Activities of Daily Living (ADL) Assessment FormAssessment · 14 questions
Questions
Send it before the visit, so patients arrive ready.
Add the Vision Therapy Initial Assessment Form to your account and make it yours in a few minutes.
Cancel anytime · BAA included