Dental History Form
Asks about last dental visit date, prior dental treatments, and periodontal health history. Built for general dentistry new patient intake documentation.
- Questions
- 12
- Pages
- 2
- Time
- about 3 min
Includes
- E-signature
- Medication list
- Conditions checklist
Your practice
Dental History Form
Page 1 of 2 · Your information
Live preview. Tap through it like a patient.
Who it is for
- General dentistry new patient intake documentation
- Periodontal practice comprehensive assessment
- Oral surgery pre-operative history collection
- Orthodontic treatment planning and records transfer
What's inside
Page 1 · Your information
- Full NameText · Required
- Last Dental Visit DateDate
- Prior Dental TreatmentsLong Text
- Periodontal Health HistoryConditions
- TMJ/TMD SymptomsLong Text
Page 2 · Additional details
- Oral Hygiene RoutineLong Text
- Dental Anxiety LevelMultiple Choice · 4 choices
- Bruxism/Nightguard UseLong Text
- Relevant Medical ConditionsConditions
- Current MedicationsMedications
From form to a ready patient
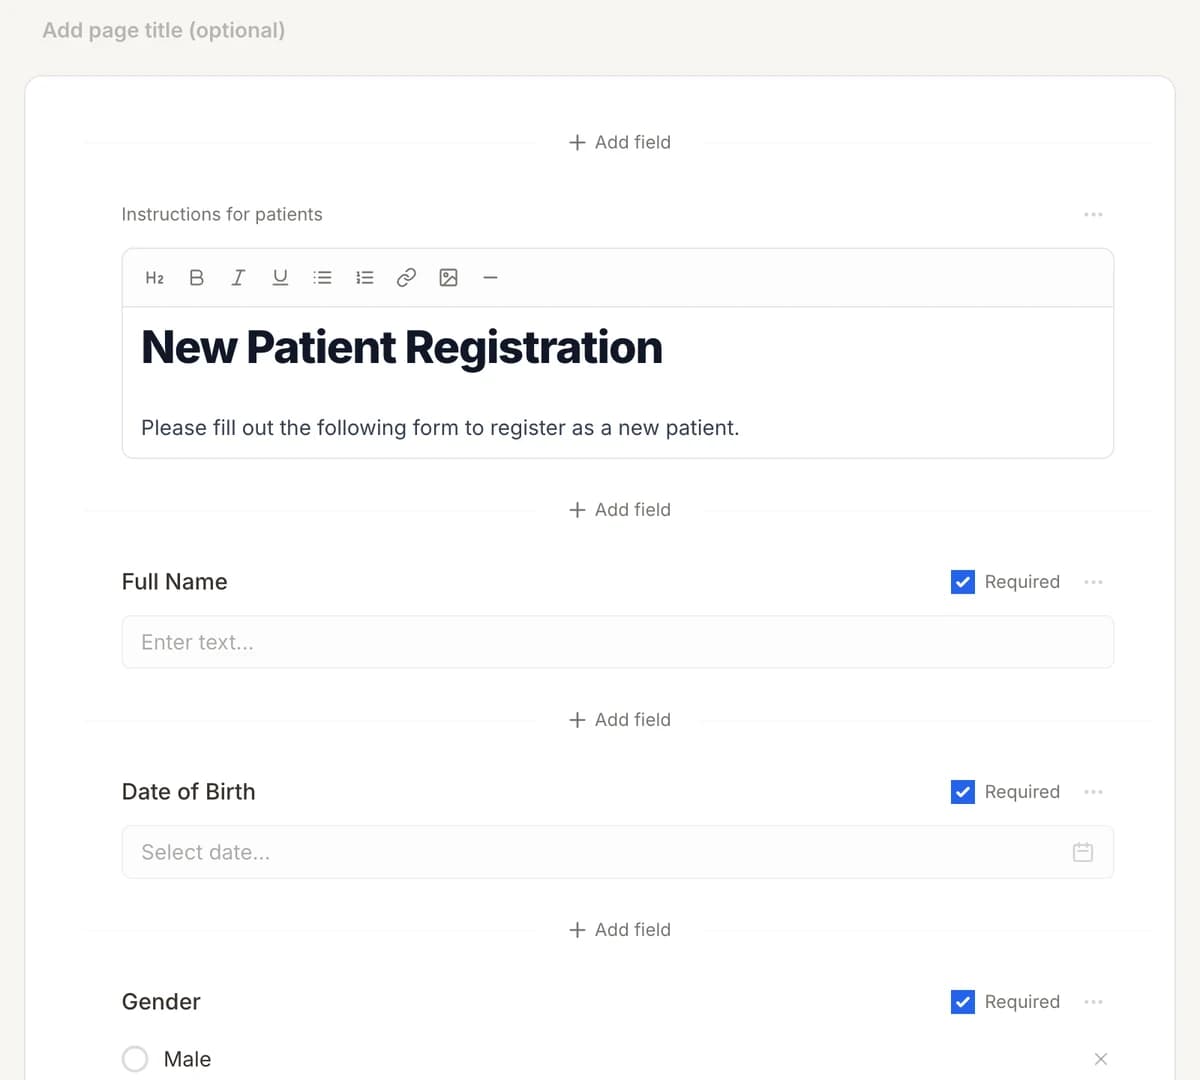
01
Make it yours
Reword, reorder, or add to the Dental History Form, and add your logo.
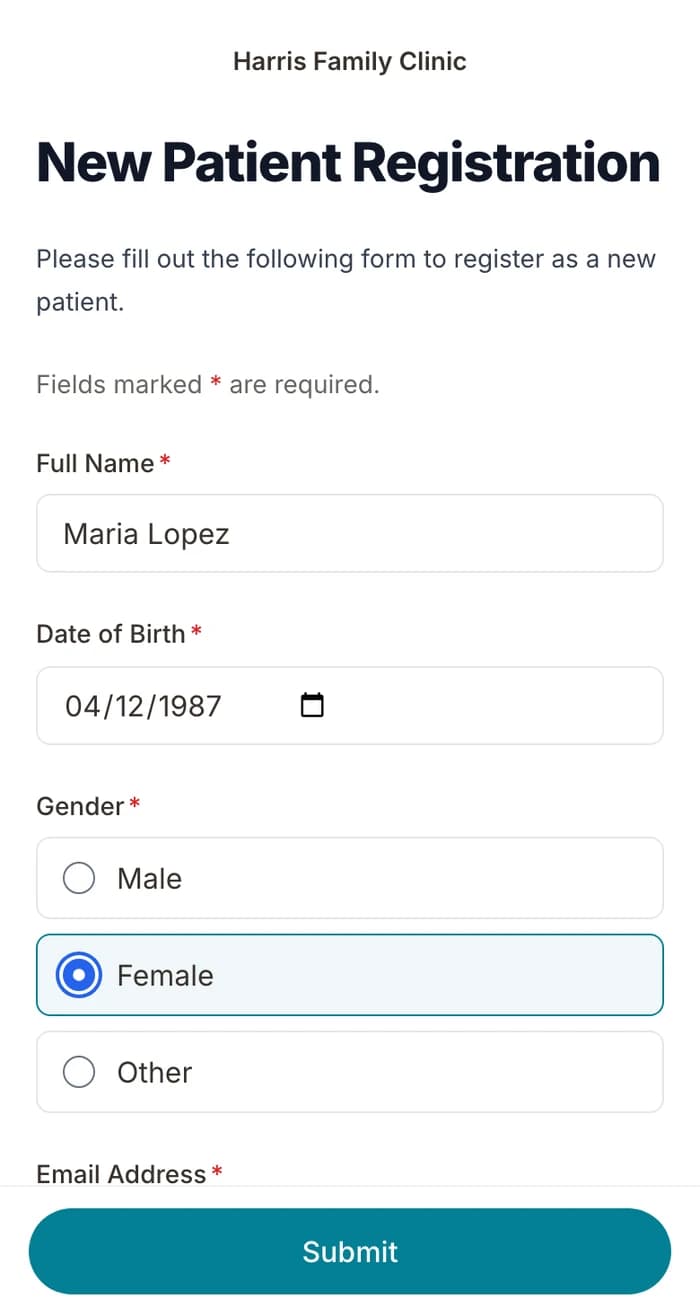
02
Patients finish it at home
A secure link by text or email, filled out on their phone before the visit. No app.
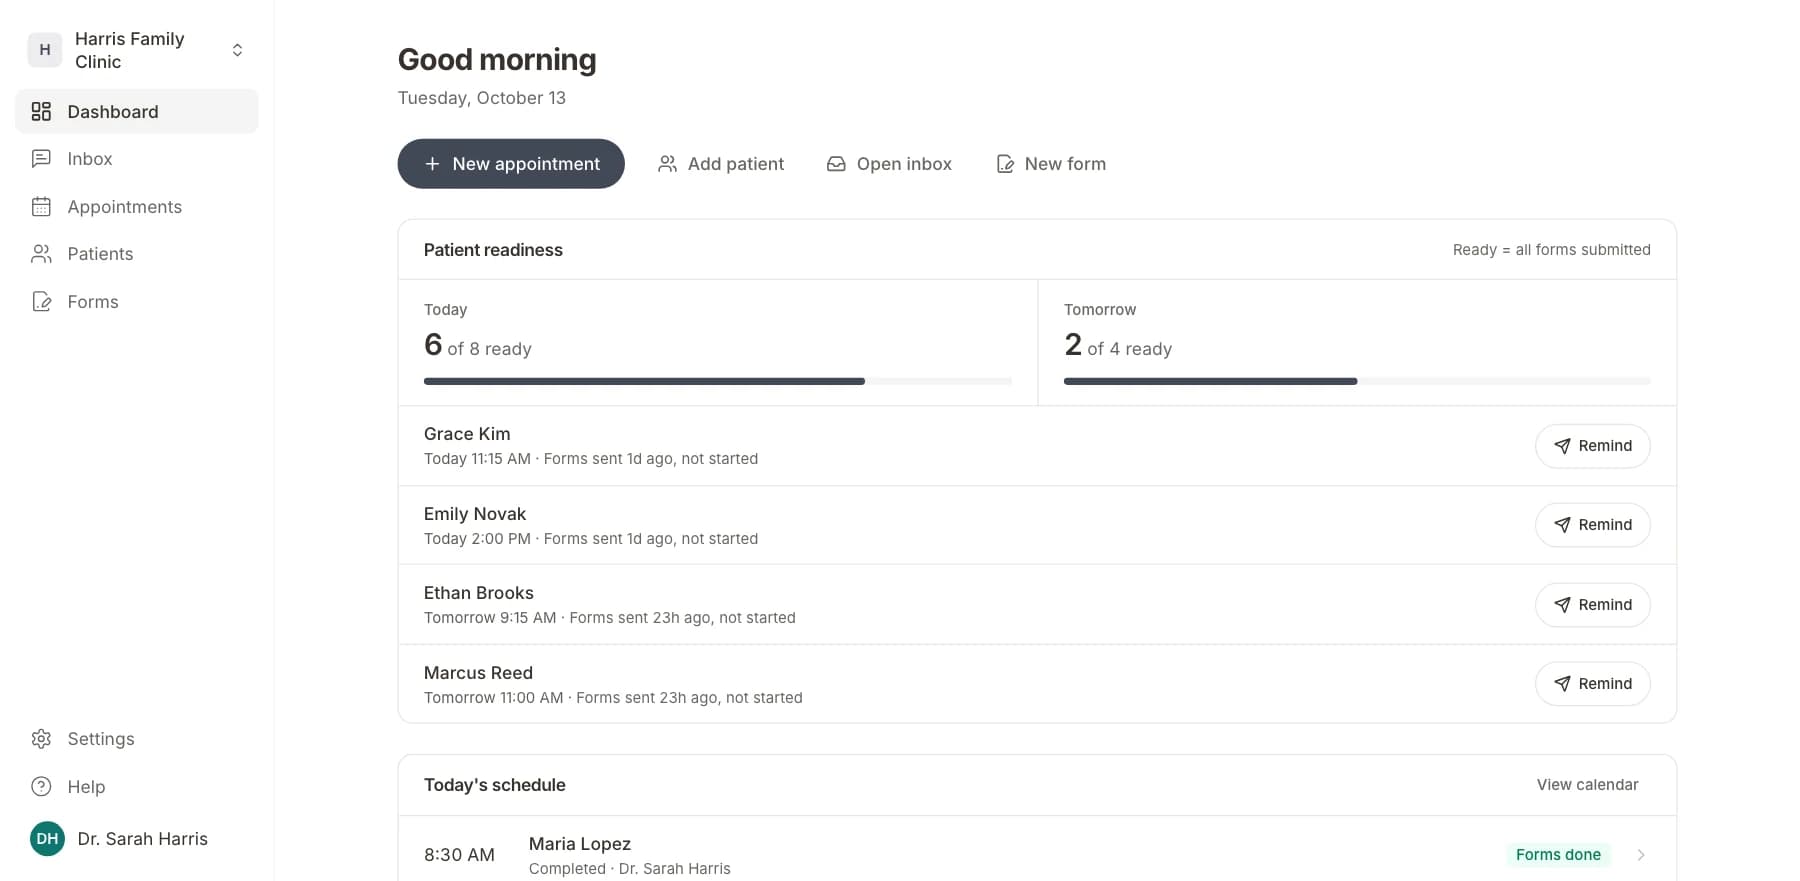
03
Your team sees who is ready
Each visit shows as ready once its forms are in. Answers land on the patient record.
Related templates
All templatesDental Patient Intake FormIntake · 20 questions
Dental Treatment ConsentConsent · 13 questions
Orthodontic Treatment Consent FormConsent · 12 questions
Pediatric Dentistry Intake FormIntake · 16 questions
Allergy History FormMedical History · 10 questions
Colonoscopy Medical HistoryMedical History · 9 questions
Questions
Send it before the visit, so patients arrive ready.
Add the Dental History Form to your account and make it yours in a few minutes.
Cancel anytime · BAA included