Workers' Compensation Intake Form
Asks about employer name, occupation, and employer phone number. Built for occupational medicine clinic intake for workplace injuries.
- Questions
- 21
- Pages
- 2
- Time
- about 5 min
Includes
- E-signature
Your practice
Page 1 of 2
Live preview. Tap through it like a patient.
Who it is for
- Occupational medicine clinic intake for workplace injuries
- Urgent care treatment of on-the-job injuries
- Orthopedic evaluation of work-related musculoskeletal injuries
- Follow-up documentation for workers' compensation claims
What's inside
Page 1
- Full NameText · Required
- Date of BirthDate · Required
- Email AddressEmail · Required
- Phone NumberPhone · Required
- Employer NameText · Required
Page 2
- Date of InjuryDate · Required
- Time of InjuryTime · Required
- Location Where Injury OccurredText · Required
- Describe How the Injury OccurredLong Text · Required
- Body Parts InjuredCheckbox · 12 choices · Required
From form to a ready patient
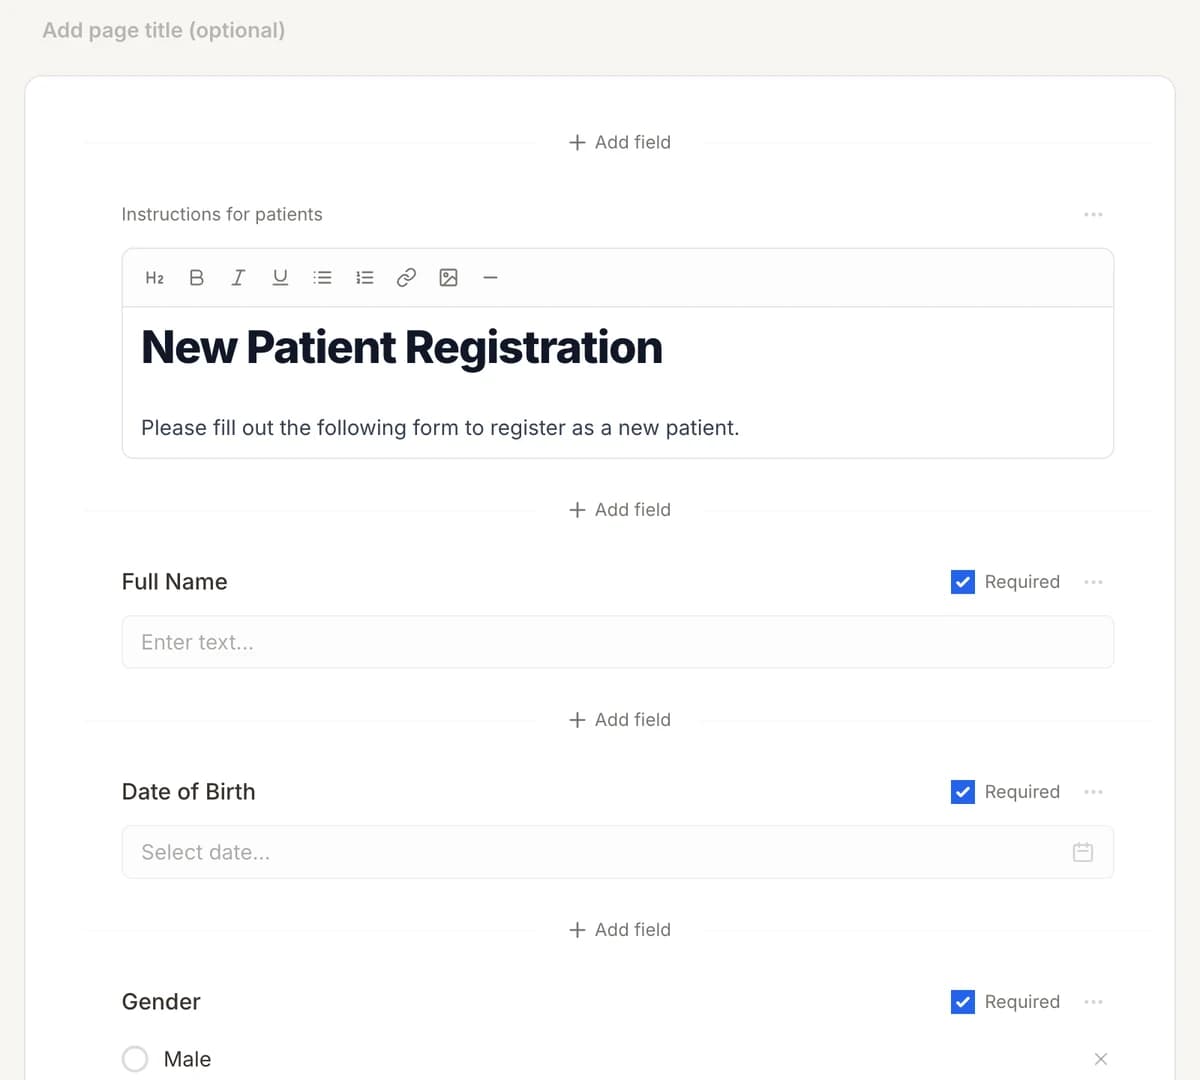
01
Make it yours
Reword, reorder, or add to the Workers' Compensation Intake Form, and add your logo.
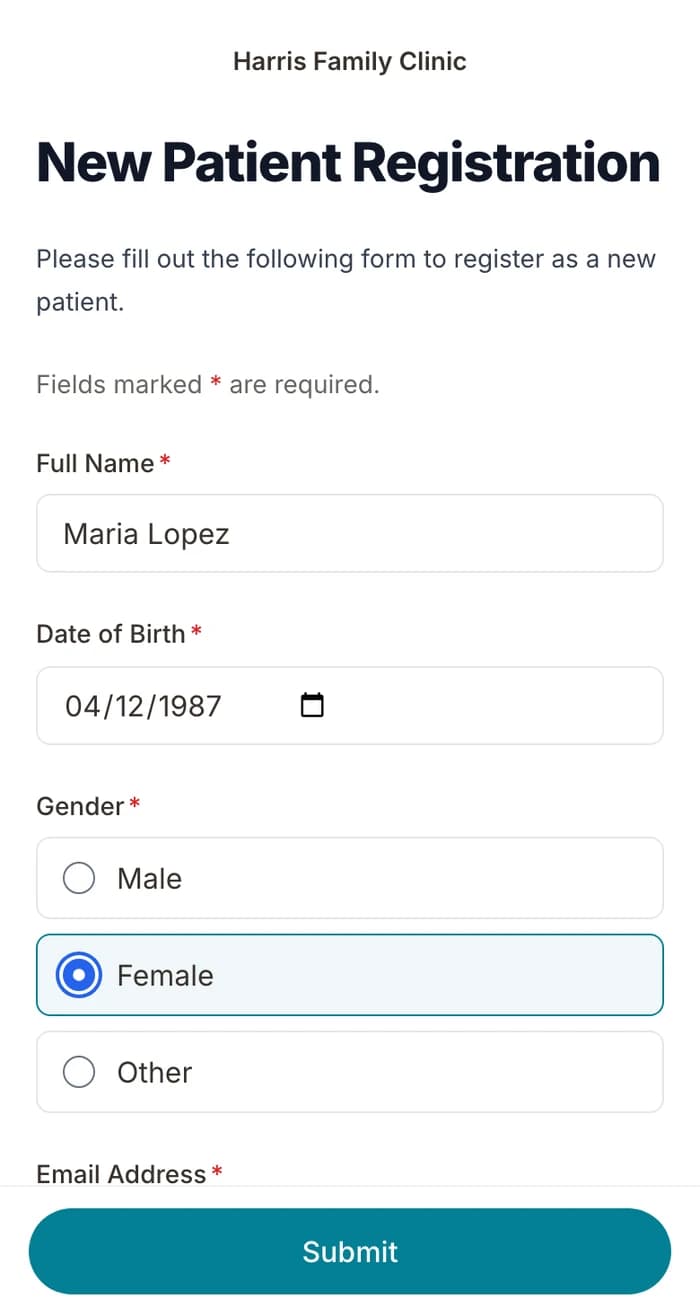
02
Patients finish it at home
A secure link by text or email, filled out on their phone before the visit. No app.
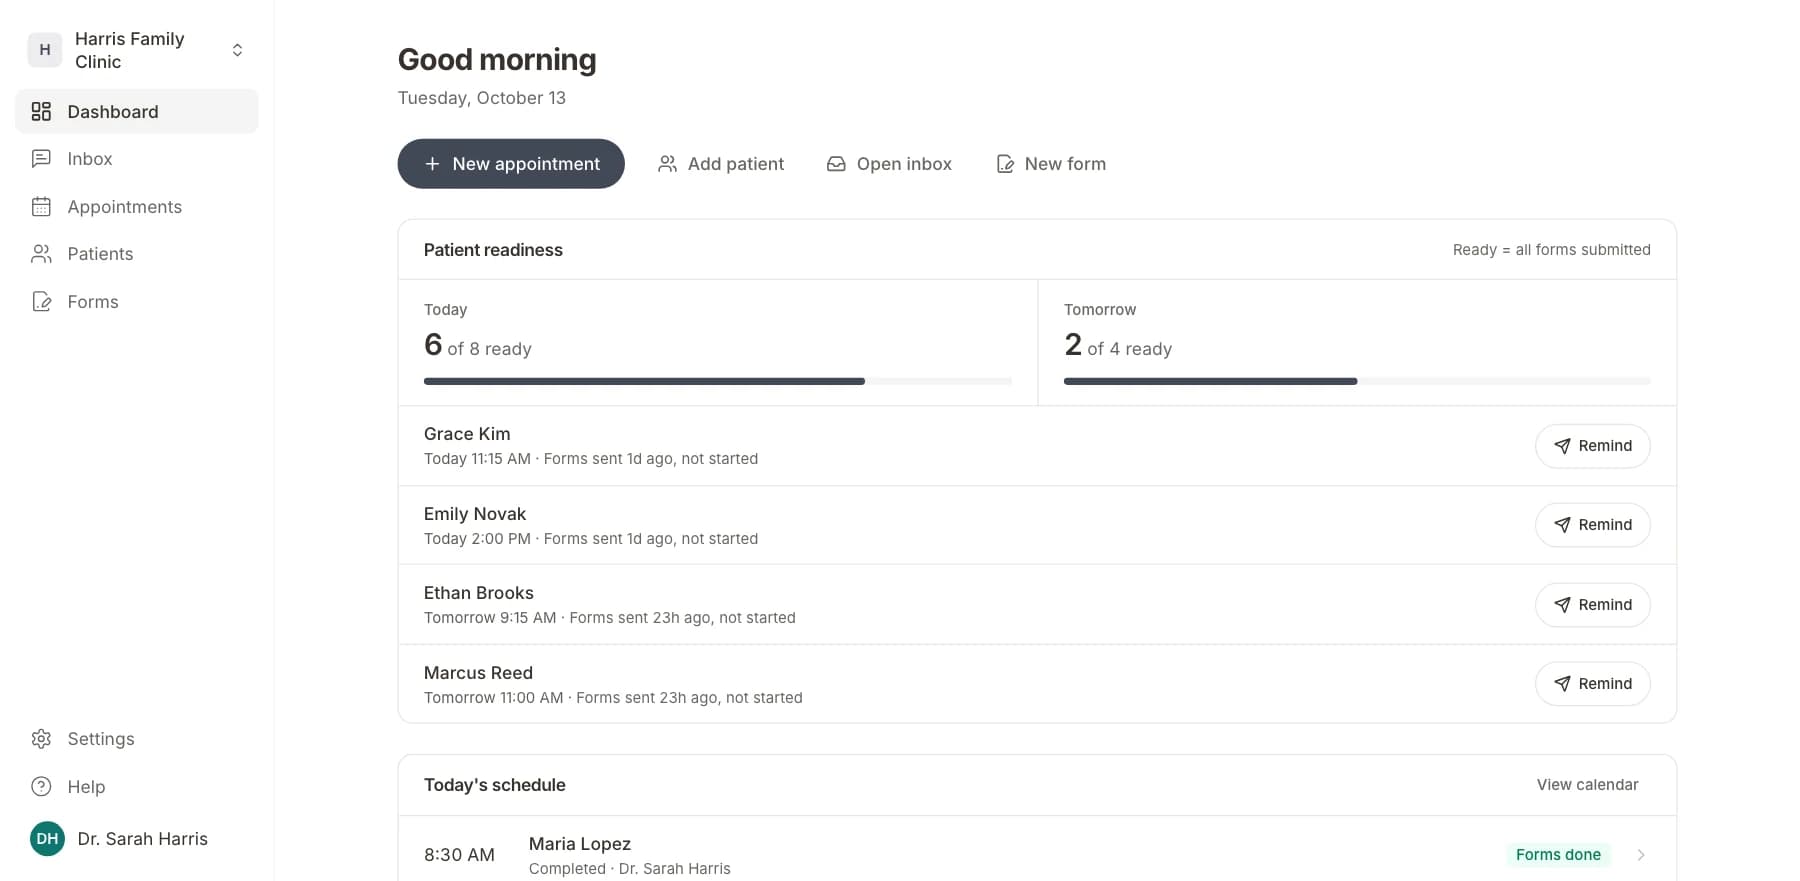
03
Your team sees who is ready
Each visit shows as ready once its forms are in. Answers land on the patient record.
Related templates
All templatesOccupational Injury History FormMedical History · 10 questions
New Patient Intake FormIntake · 18 questions
Occupational Health History FormMedical History · 14 questions
Corporate Wellness Screening FormScreening · 12 questions
Advance Directive FormRegistration · 14 questions
Appointment Request FormRegistration · 11 questions
Questions
Send it before the visit, so patients arrive ready.
Add the Workers' Compensation Intake Form to your account and make it yours in a few minutes.
Cancel anytime · BAA included